KMDS

 E-submission

Articles
- Page Path
- HOME > J Mov Disord > Volume 17(1); 2024 > Article
-
Case Report
A New Phenotype of TUBB4A Mutation in a Family With Adult-Onset Progressive Spastic Paraplegia and Isolated Hypomyelination Leukodystrophy: A Case Report and Literature Review -
Pei-Chen Hsieh1
 , Pei Shan Yu1, Wen-Lang Fan2,3, Chun-Chieh Wang1, Chih-Ying Chao1, Yih-Ru Wu1,4

-
Journal of Movement Disorders 2024;17(1):94-98.
DOI: https://doi.org/10.14802/jmd.23142
Published online: October 23, 2023
1Department of Neurology, Chang Gung Memorial Hospital, Linkou Medical Center, Taoyuan, Taiwan
2Department of Medical Research, Kaohsiung Chang Gung Memorial Hospital, Kaohsiung, Taiwan
3Genomic Medicine Core Laboratory, Chang Gung Memorial Hospital, Linkou Medical Center, Taoyuan, Taiwan
4Department of Neurology, College of Medicine, Chang Gung University, Taoyuan, Taiwan
- Corresponding author: Yih-Ru Wu, MD Department of Neurology, Chang Gung Memorial Hospital, Linkou Medical Center, College of Medicine, Chang Gung University, No. 5, Fuxing Street, Taoyuan 33305, Taiwan / Tel: +886-3-3281200 Ext. 8349 / Fax: +886-3-328722 / E-mail: yihruwu@cgmh.org.tw
• Received: July 26, 2023 • Revised: September 25, 2023 • Accepted: October 23, 2023
Copyright © 2024 The Korean Movement Disorder Society
This is an Open Access article distributed under the terms of the Creative Commons Attribution Non-Commercial License (http://creativecommons.org/licenses/by-nc/4.0/) which permits unrestricted non-commercial use, distribution, and reproduction in any medium, provided the original work is properly cited.


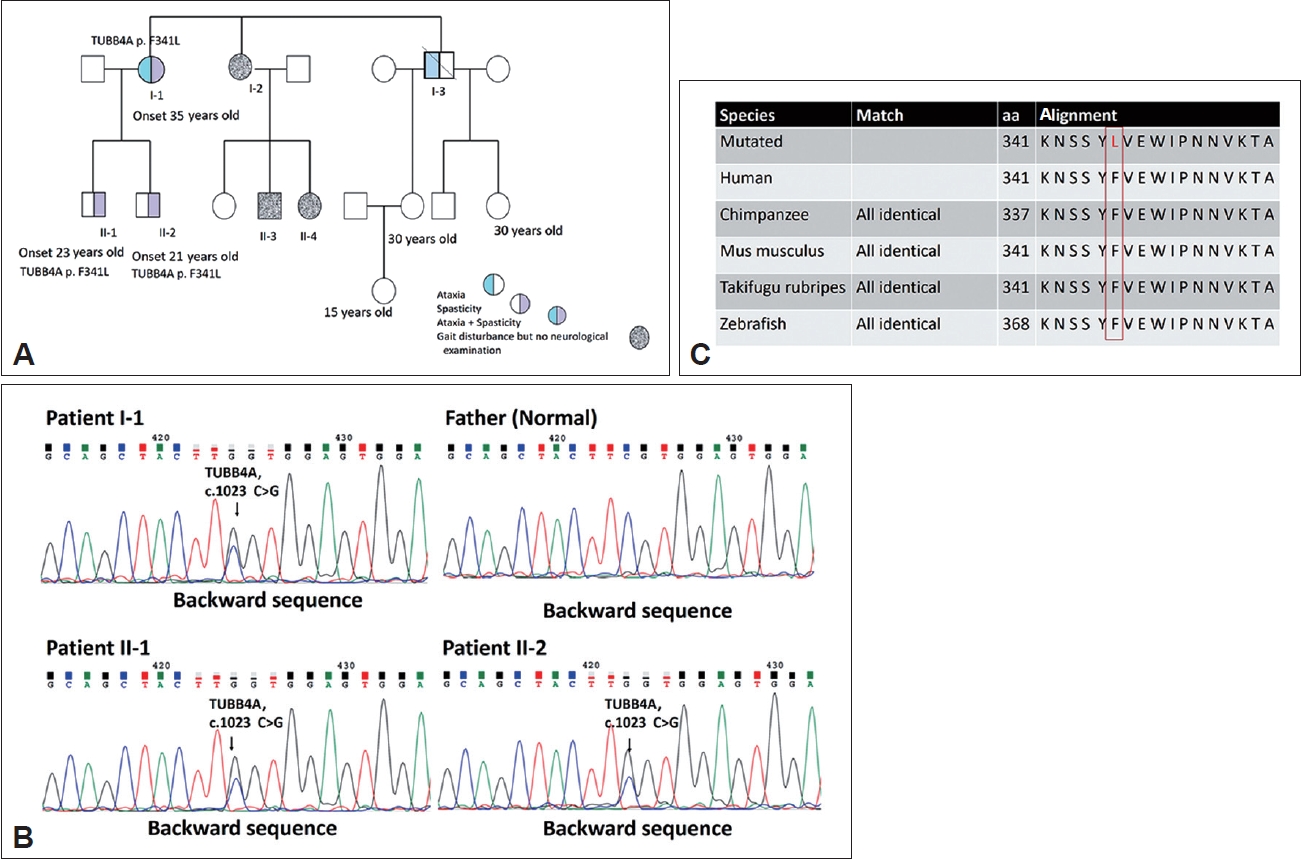

Figure & Data
References
Citations
Citations to this article as recorded by 
- The role of genetics and molecular mechanisms in early onset scoliosis
Shuang Feng, Yichen Du, Siu Wai Choi, Kelvin Sin Chi Cheung, Jason Pui Yin Cheung, Zezhou Su
Journal of Clinical Orthopaedics and Trauma.2026; 73: 103340. CrossRef
Comments on this article
 PubReader
 ePub Link
 Cite
 XML Download
A New Phenotype of TUBB4A Mutation in a Family With Adult-Onset Progressive Spastic Paraplegia and Isolated Hypomyelination Leukodystrophy: A Case Report and Literature Review
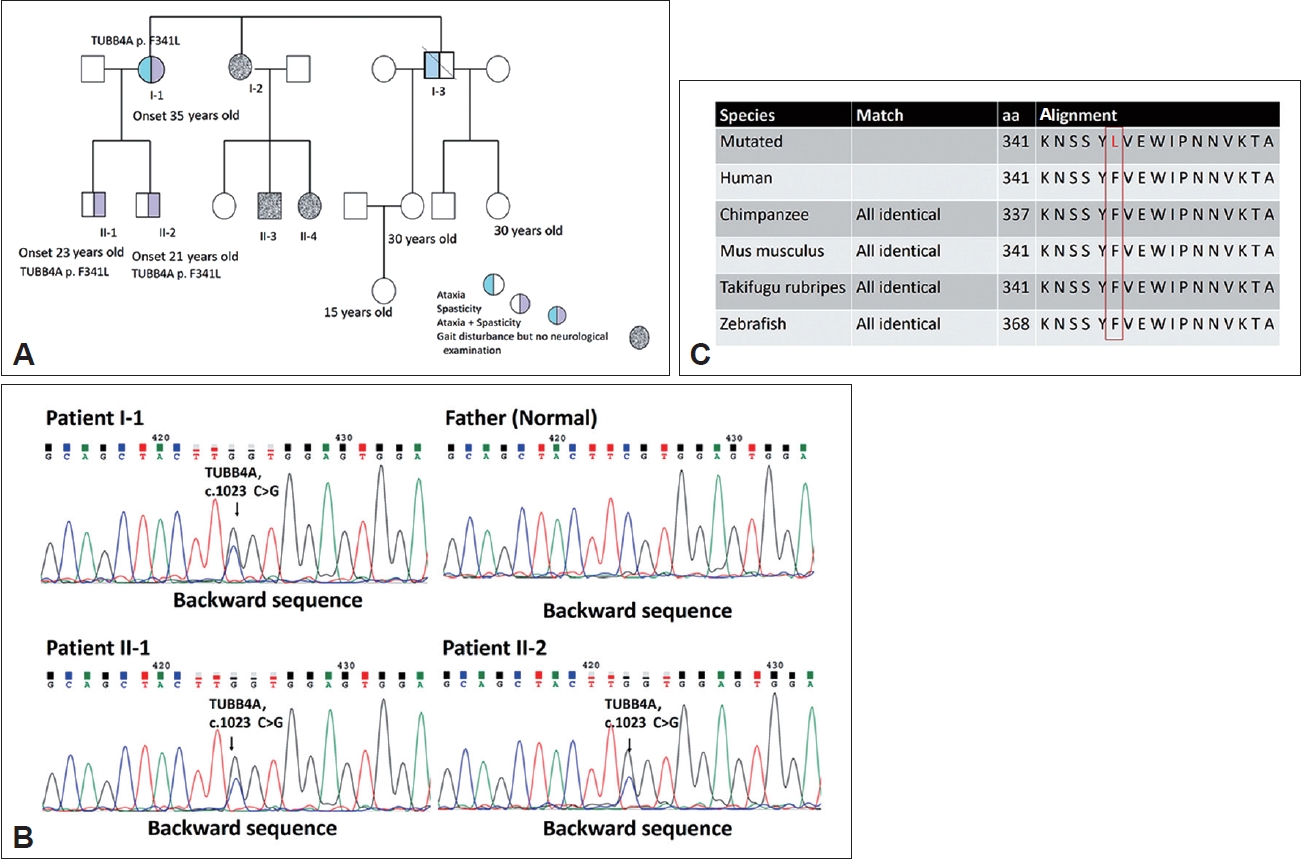
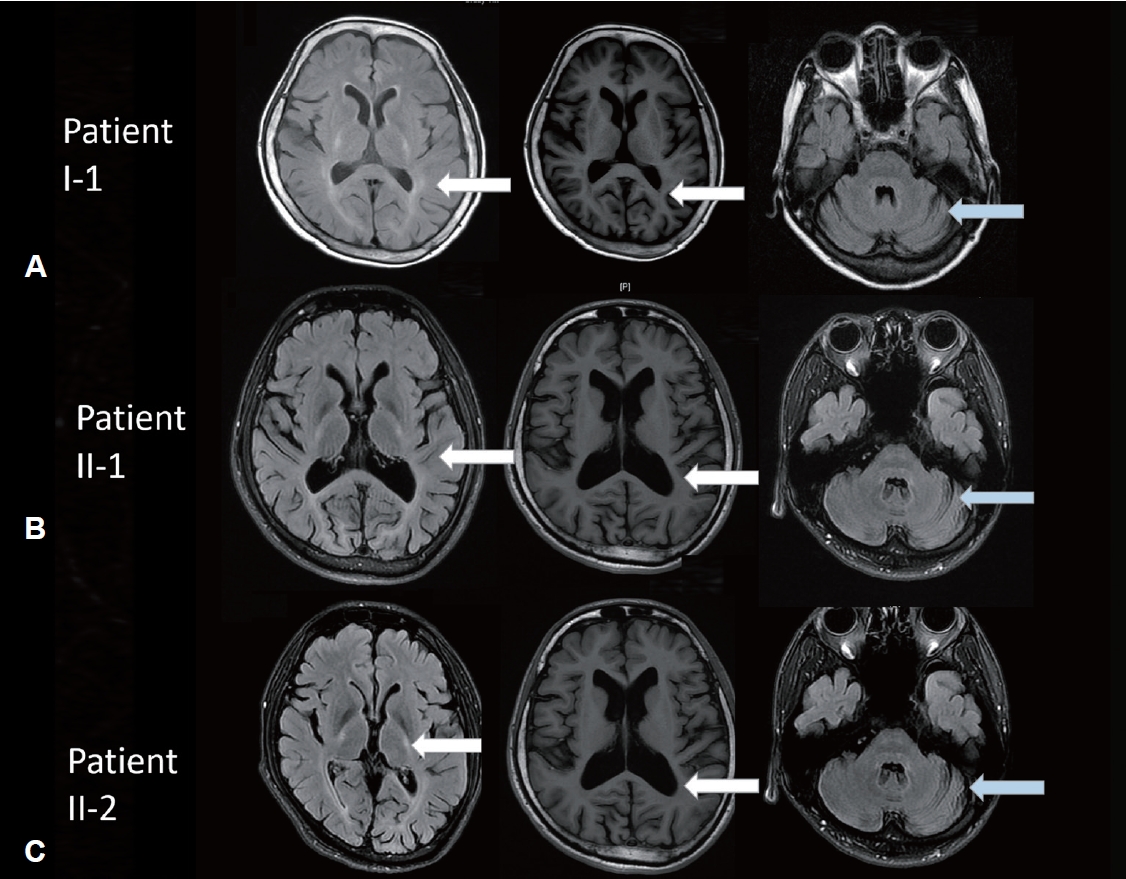
Figure 1. Pedigree and characterization of the p.F341L mutation of TUBB4A. A: Family pedigree. Blue symbols denote affected individuals with ataxia, purple symbols denote individuals with spasticity, and open symbols denote unaffected individuals. B: Sanger testing of the polymerase chain reaction products show the p.F341L variant in the family members, demonstrating that the variant is a maternally inherited splicing variant. C: Comparison of amino acid sequences across different species revealed the conservation of altered residues. Red box indicates missense mutation.
Figure 2. Brain MRI in individuals with TUBB4A mutations. A: At age 50, Patient I-1 exhibited hyperintensity in the T2 axial FLAIR sequence and isodensity in the T1 axial, primarily located in the posterior limbs of the internal capsule, and diffuse posterior predominant hyperintensity (white arrows). Cerebellar atrophy was evident (light blue arrow), but the putamen and basal ganglia were preserved. B: At age 38, Patient II-1 exhibited generalized brain atrophy and hyperintensity in the T2 axial FLAIR sequence and isodenisty in T1 axial, primarily located in the subcortical parietal and occipital lobes (white arrows). The cerebellar (light blue arrow), putamen, and basal ganglia were preserved. C: At age 34, Patient II-2 exhibited hyperintensity in the T2 axial FLAIR sequence and isodenisty in T1 axial, primarily located in the posterior limbs of the internal capsule and subcortical parietal lobes (white arrows). The cerebellar (light blue arrow), putamen, and basal ganglia were preserved. MRI, magnetic resonance imaging; FLAIR, fluid attenuated inversion recovery.
Figure 1.
Figure 2.
A New Phenotype of TUBB4A Mutation in a Family With Adult-Onset Progressive Spastic Paraplegia and Isolated Hypomyelination Leukodystrophy: A Case Report and Literature Review